

Tesamorelin shrank deep belly fat by about 15% in trials, but the scale didn't move and the fat came back after stopping
Evidence check, October 5, 2026
The claim: "Tesamorelin is the FDA-approved peptide that melts stubborn belly fat and builds muscle."
Our grade: Promising. It really does shrink the deep fat around the organs, in good trials. But nearly all of that evidence is in people with HIV, it is not a weight-loss drug, and it only works while you keep taking it.

Sam is 35. He runs twice a week and his arms and legs are lean, but his belt sits two holes looser than it did at 25. A wellness clinic near him lists tesamorelin on its menu: "the FDA-approved peptide for stubborn belly fat."
Would it flatten his stomach, and would it stay flat?
The answer matters because tesamorelin is the best-tested of the growth-hormone peptides in our guide to 22 peptides. If any of that group is worth the money, it should be this one.
Where the claim came from
Tesamorelin is a copy of the signal your brain sends to make the body release its own growth hormone. The FDA approved it in 2010 as Egrifta, a daily shot under the skin, for one group: adults with HIV whose medicines had left them with a hard, swollen belly. A newer version, Egrifta WR, was approved in March 2025 [5].
Then it moved to the clinics. Andrew Huberman covered it in an April 2024 episode on peptides, in a section on drugs that raise growth hormone [15]. Clinics now sell it to people without HIV for belly fat, muscle, sleep and a sharper mind. The approval is real. The question is how far it stretches.
It shrinks the fat you can't pinch
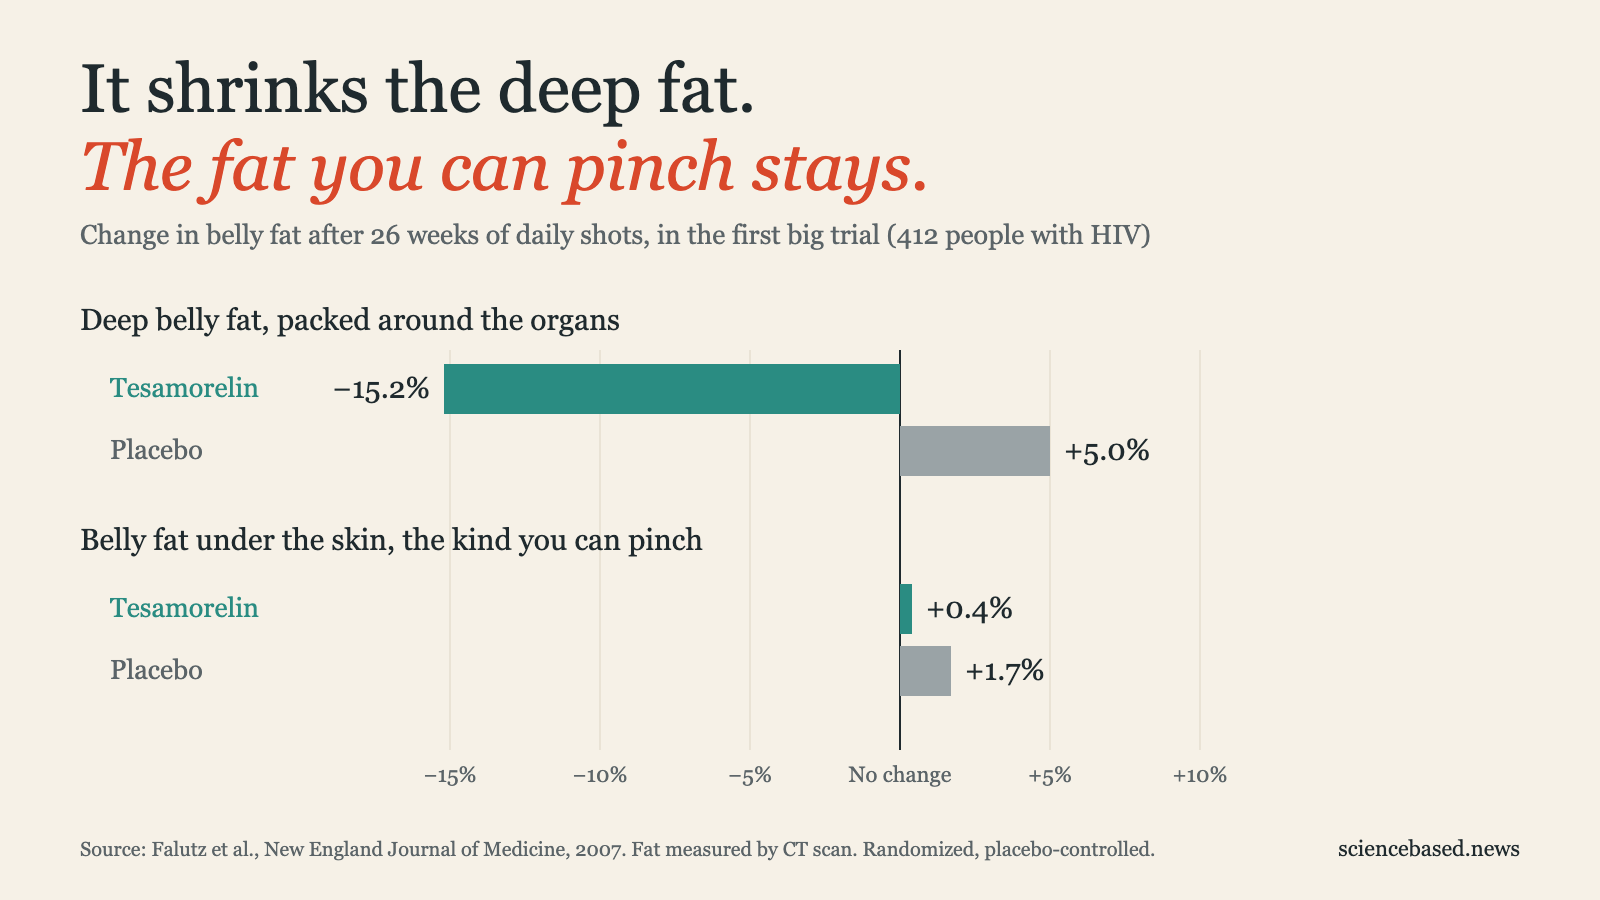
There are two kinds of belly fat. One sits under the skin, where you can pinch it. The other is packed deep around the liver and gut. The deep kind is the one linked to heart disease and diabetes.
Tesamorelin works on the deep kind. In the first big trial, 412 people with HIV were randomly assigned to a daily shot or a placebo for 26 weeks. Deep belly fat fell 15.2% on the drug and rose 5.0% on placebo [1]. A second trial of 404 people found the same direction [4]. Pooled, the two trials covered 806 people, and the drug cut deep fat by 15.4% more than placebo [2]. The maker, Theratechnologies, ran both.
The fat you can pinch did not change [2].
The scale didn't move
Here is the first surprise. The FDA label says tesamorelin is "not indicated for weight loss management as it has a weight neutral effect" [5]. People lost deep fat and weighed the same.
Where did the weight go? Into lean mass, which rose about 1.2 to 1.3 kg (2.6 to 2.9 pounds) on the drug [5]. That sounds like muscle. But lean mass on a body scan counts water too, and growth hormone makes the body hold water. Swelling and joint pain are on the label as side effects for that reason [5].
One analysis did look at muscle itself. In people from the two trials whose belly fat had responded, trunk muscles were slightly larger and less fatty on scans [12]. Nobody measured whether they were stronger. No published trial has tested tesamorelin for strength.
So the waist shrank a little. After a year on the drug it was 3.4 cm (1.3 inches) smaller [2]. A real change, and a modest one.
What happened when people stopped
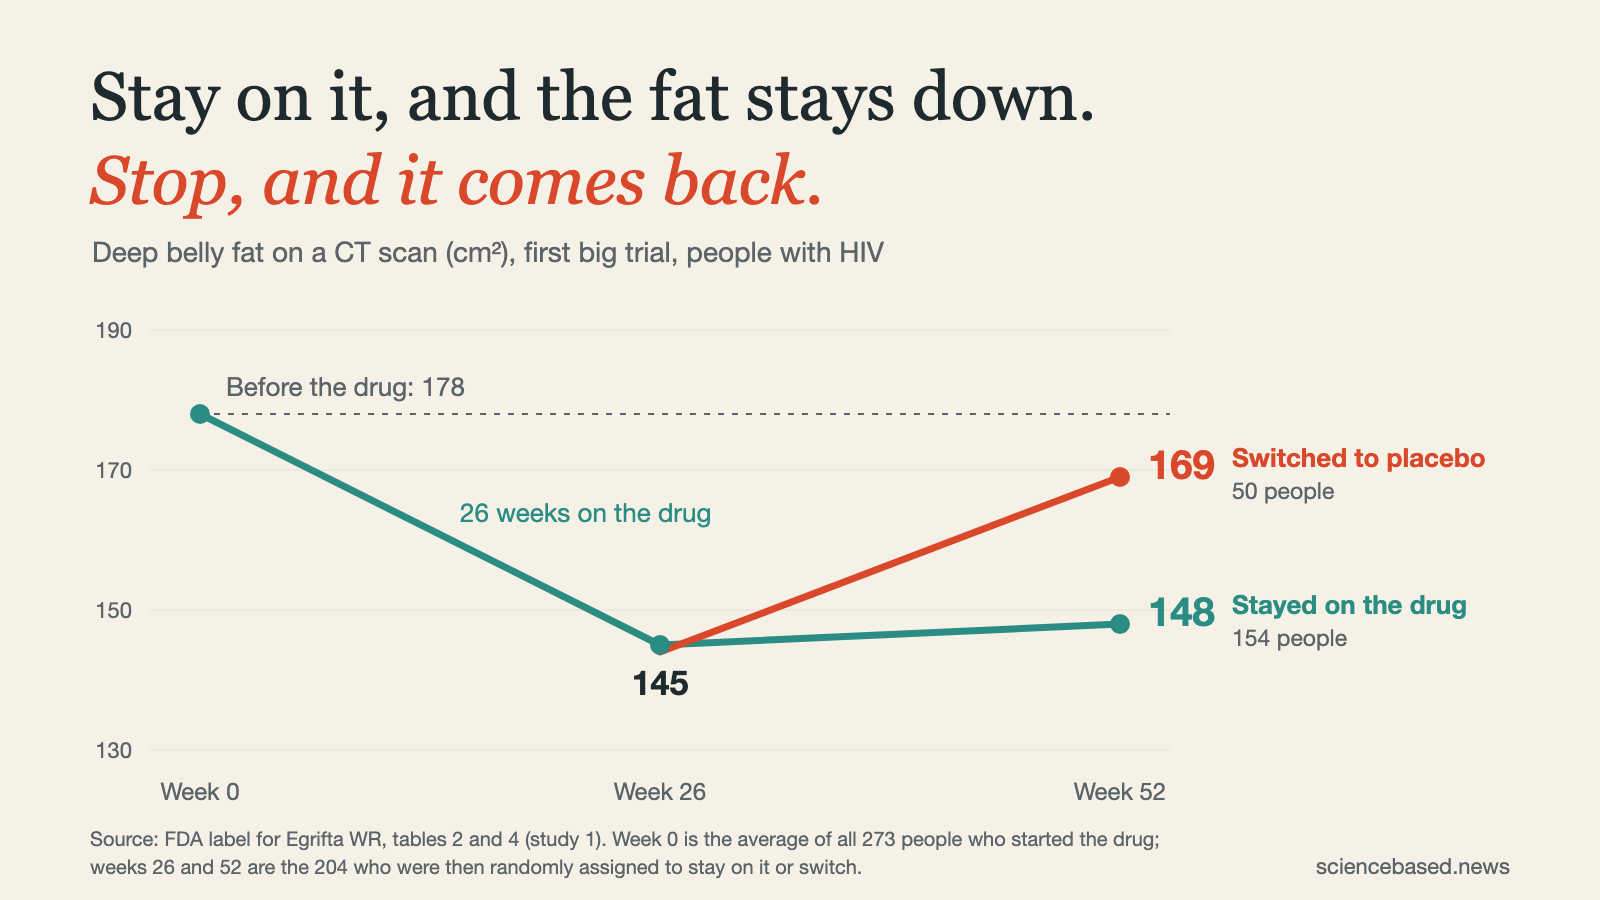
At 26 weeks, the first trial did something useful. It took some of the people on tesamorelin and switched them to placebo without telling them [3].
Those who stayed on the drug kept their loss: deep fat was down about 18% at one year. In those who were switched, it came back. The second trial saw the same thing, and its authors wrote that the gains "were rapidly lost" [4]. The first trial's authors put it plainly: the effects "do not last beyond the duration of treatment" [3].
That is the punchline. Tesamorelin does not reset your belly. It holds the fat down for as long as you inject it every day, and within six months of stopping you are back where you began.
Outside HIV, the evidence gets thin
Sam doesn't have HIV. What is there for him?
One trial. Researchers funded by the US National Institutes of Health gave tesamorelin or placebo to 60 adults with belly obesity and low growth hormone for 12 months. Deep fat fell 16 cm² on the drug and rose 19 cm² on placebo, triglycerides fell, and blood sugar did not change [6]. It is a good small trial. Nobody has repeated it.
There are two other human findings worth knowing. In people with HIV and fatty liver, a 61-person randomized trial found that 35% on tesamorelin got their liver fat back under the normal line in a year, against 4% on placebo [8]. An earlier 50-person trial pointed the same way [7].
The brain claim is weaker. A randomized trial in 152 adults aged 55 to 87 found better scores on planning and attention tests after 20 weeks [9]. But two later trials did not back it up: one in 73 people with HIV found no difference in thinking scores after six months [10], and a 22-person pilot found no change in thinking, sleep, fatigue or physical performance after 10 weeks [11].
So back to Sam's belt. The drug would probably shrink his deep belly fat somewhat while he took it. The evidence for that in someone like him is one trial of 60 people. He would not weigh less, nobody knows if he would be stronger, and the fat would come back when he stopped.
Our grade
| Claim | Evidence | Grade |
|---|---|---|
| Shrinks deep belly fat in people with HIV | Two randomized trials, 806 people, 26 to 52 weeks | Solid |
| Shrinks deep belly fat in people without HIV | One randomized trial, 60 people, 12 months | Promising |
| The fat stays off after you stop | Two trials switched people to placebo; the fat came back | Not supported |
| Lowers your weight | Trials and the FDA label: no change in weight | Not supported |
| Builds muscle and strength | Lean mass up 1.2 to 1.3 kg, partly water; no strength trial | Unproven |
| Sharpens thinking | One positive trial of 152; two later trials found nothing | Weak |
The case for the other side: deep belly fat is the dangerous kind, and few things shrink it without also shrinking muscle. A 2026 analysis pooling five randomized trials confirmed less deep fat, less liver fat and more lean mass [14]. If a longer trial showed fewer heart attacks, this grade would rise. None has. The label says long-term heart safety "has not been established" [5].
What this means for you
If you have HIV and a hard belly from your medicines, this is what the drug was approved for. Ask your HIV doctor about it.
If you don't have HIV, know what you would be buying: a daily shot, for as long as you want the effect, backed by one 60-person trial. Deep belly fat also responds to things with far more evidence. Exercise and modest weight loss shrink it, and the GLP-1 drugs do too, with trials in tens of thousands of people. See our checks on the GLP-1 pills and retatrutide.
If you still want to try it, three points from the label are worth raising with a doctor first [5]:
- Blood sugar. In the HIV trials, 5% of people on the drug crossed the line for diabetes on a blood test, against 1% on placebo. Trials in people without HIV [6] and in 53 people who already had type 2 diabetes [13] did not see blood sugar worsen, but they were small.
- Cancer. The drug raises IGF-1, a growth signal, above the normal range in many people. It is not for anyone with an active cancer, and the label says the effect of keeping IGF-1 high for years is unknown.
- The product. The trials tested Egrifta, a prescription drug. Ask the clinic exactly what is in the vial and where it was made.
And if muscle is the goal, lift. See how much protein you need.
In the trials, what happened to body weight on tesamorelin?
People lost deep belly fat and gained lean mass, some of it water, so the scale stayed put. The FDA label calls the drug "weight neutral".
What happened to the deep belly fat when people were switched to placebo?
Two trials switched people to placebo at six months, and the fat returned. The effect lasts only while you take the drug.
How much trial evidence is there for belly fat in people without HIV?
The 806 people were all living with HIV. Outside HIV there is one 12-month trial of 60 adults.
Which kind of belly fat does tesamorelin shrink?
Deep belly fat fell about 15%. The fat under the skin did not change.
What's next
The strength question may finally get an answer. A randomized trial called TRIUMPH is giving tesamorelin or placebo, on top of an exercise program, to 100 adults aged 50 to 80 with HIV who are frail or close to it. It will measure physical function and muscle, with main results listed for 2028 [16]. No large trial in people without HIV is registered.
This is the first of our one-by-one checks on the peptides in the guide. Next is CJC-1295, which is sold to do the same job with far less evidence. Related: peptides: GLP-1s, BPC-157 and epitalon, keeping muscle on GLP-1 drugs.
Was this helpful?
Sources
- Falutz J, Allas S, Blot K, et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. N Engl J Med, 2007. 412 people with HIV, randomized, placebo-controlled, 26 weeks. Run by Theratechnologies. doi:10.1056/NEJMoa072375
- Falutz J, Mamputu JC, Potvin D, et al. Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in human immunodeficiency virus-infected patients with excess abdominal fat: a pooled analysis of two multicenter, double-blind placebo-controlled phase 3 trials with safety extension data. J Clin Endocrinol Metab, 2010. 806 people with HIV, two randomized trials pooled, 26 weeks plus a 26-week extension. Run by Theratechnologies. doi:10.1210/jc.2010-0490
- Falutz J, Allas S, Mamputu JC, et al. Long-term safety and effects of tesamorelin, a growth hormone-releasing factor analogue, in HIV patients with abdominal fat accumulation. AIDS, 2008. 52-week extension of the first trial; people on the drug were re-randomized to stay on it or switch to placebo. Run by Theratechnologies. doi:10.1097/QAD.0b013e32830a5058
- Falutz J, Potvin D, Mamputu JC, et al. Effects of tesamorelin, a growth hormone-releasing factor, in HIV-infected patients with abdominal fat accumulation: a randomized placebo-controlled trial with a safety extension. J Acquir Immune Defic Syndr, 2010. 404 people with HIV, randomized, 6 months plus a 6-month extension. Run by Theratechnologies. doi:10.1097/QAI.0b013e3181cbdaff
- US Food and Drug Administration. Egrifta WR (tesamorelin) prescribing information, 2026. DailyMed
- Makimura H, Feldpausch MN, Rope AM, et al. Metabolic effects of a growth hormone-releasing factor in obese subjects with reduced growth hormone secretion: a randomized controlled trial. J Clin Endocrinol Metab, 2012. 60 adults without HIV, randomized, double-blind, 12 months. NIH funded. doi:10.1210/jc.2012-2794
- Stanley TL, Feldpausch MN, Oh J, et al. Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation: a randomized clinical trial. JAMA, 2014. 50 people with HIV, randomized, double-blind, 6 months. NIH funded. doi:10.1001/jama.2014.8334
- Stanley TL, Fourman LT, Feldpausch MN, et al. Effects of tesamorelin on non-alcoholic fatty liver disease in HIV: a randomised, double-blind, multicentre trial. Lancet HIV, 2019. 61 people with HIV and fatty liver, randomized, 12 months. NIH funded. doi:10.1016/S2352-3018(19)30338-830338-8)
- Baker LD, Barsness SM, Borson S, et al. Effects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults: results of a controlled trial. Arch Neurol, 2012. 152 adults aged 55 to 87, randomized, double-blind, 20 weeks. NIH funded. doi:10.1001/archneurol.2012.1970
- Ellis RJ, Vaida F, Hu K, et al. Effects of tesamorelin on neurocognitive impairment in persons with HIV and abdominal obesity. J Infect Dis, 2025. 73 people with HIV, randomized, open-label (no placebo), 6 months. doi:10.1093/infdis/jiaf012
- Stewart CE, French KP, Wright TJ, et al. The effect of growth hormone-releasing hormone on cognition and brain connectivity in adults with cognition ranging from normal to mild cognitive impairment. eNeurologicalSci, 2026. 22 adults, double-blind, placebo-controlled pilot, 10 weeks. doi:10.1016/j.ensci.2026.100616
- Adrian S, Scherzinger A, Sanyal A, et al. The growth hormone releasing hormone analogue, tesamorelin, decreases muscle fat and increases muscle area in adults with HIV. J Frailty Aging, 2019. Secondary analysis of the two phase 3 trials, 341 people, limited to those whose belly fat responded. doi:10.14283/jfa.2018.45
- Clemmons DR, Miller S, Mamputu JC. Safety and metabolic effects of tesamorelin, a growth hormone-releasing factor analogue, in patients with type 2 diabetes: a randomized, placebo-controlled trial. PLoS One, 2017. 53 people with type 2 diabetes, randomized, 12 weeks. Run by Theratechnologies. doi:10.1371/journal.pone.0179538
- Badran AS, Helal A, Shata KS, et al. Body composition, hepatic fat, metabolic, and safety outcomes of tesamorelin, a GHRH analogue, in HIV-associated lipodystrophy: a meta-analysis of randomized controlled trials. Obes Res Clin Pract, 2026. Five randomized trials in people with HIV. doi:10.1016/j.orcp.2026.01.002
- Huberman A. Benefits & risks of peptide therapeutics for physical & mental health. Huberman Lab podcast, April 1, 2024. hubermanlab.com
- Erlandson KM, Gustafson L, Johnson JE, et al. Tesamorelin as an adjunct to exercise for improving physical function in HIV (TRIUMPH): a clinical trial protocol. BMJ Open, 2026. Protocol for a 100-person randomized, double-blind trial. doi:10.1136/bmjopen-2026-120740; NCT06554717